
Diabetic foot ulcers and diabetic foot infections are closely related, but they are not the same condition. A foot ulcer is an open wound that develops because of tissue damage, often associated with neuropathy, pressure, or poor circulation. An infected wound occurs when microorganisms invade tissue and cause a clinical infection.
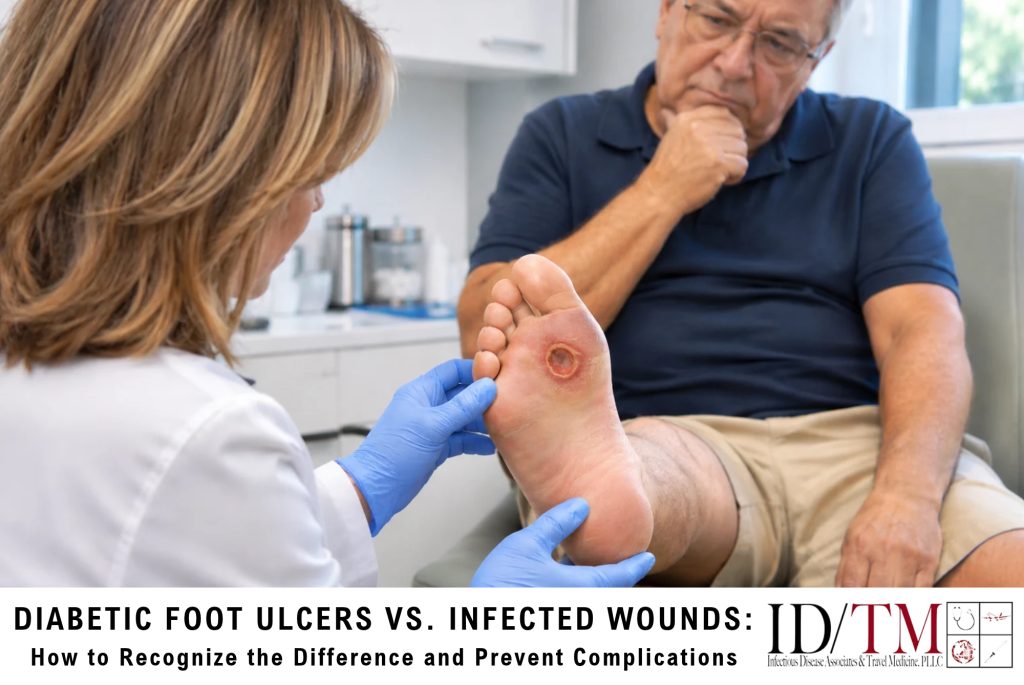
Understanding this distinction is essential because not every diabetic foot ulcer requires antibiotics, but every diabetic foot ulcer requires appropriate evaluation and wound care.
When infection develops, treatment becomes more complex. Bacteria can spread into deeper tissues, including tendons, joints, and bones. Severe infections can lead to hospitalization, tissue loss, or amputation.
At Infectious Disease Associates and Travel Medicine, patients in Gainesville, Lake City, and surrounding North Central Florida communities can receive specialized care for diabetic foot infections, nonhealing ulcers, and related complications.
What Is a Diabetic Foot Ulcer?
A diabetic foot ulcer is an open wound involving the skin and potentially deeper tissues of the foot.
Ulcers commonly develop on areas exposed to repetitive pressure, such as the bottom of the foot, heel, or toes.
How Diabetic Foot Ulcers Develop
Diabetic neuropathy can reduce protective sensation, making it difficult to recognize pressure, friction, or minor injuries.
Repeated pressure can damage tissue beneath a callus or create a blister that eventually becomes an open wound.
Poor circulation can further impair healing.
Common Risk Factors
Factors that increase the likelihood of diabetic foot ulcers include peripheral neuropathy, peripheral artery disease, previous ulcers, foot deformities, poorly fitting footwear, and inadequate pressure relief.
A history of a previous foot ulcer or amputation is particularly important because it identifies patients at increased risk of future complications.
What Is an Infected Diabetic Foot Wound?
An infected diabetic foot wound occurs when bacteria invade tissue and produce clinical signs of infection.
Bacteria can be present on the surface of an ulcer without causing infection.
This distinction is important because antibiotics should target clinically meaningful bacterial infection, not simply bacterial colonization.
Colonization vs. Infection
Colonization means microorganisms are present without causing an invasive infection.
Most chronic open wounds contain some microorganisms.
Clinical infection is diagnosed when bacteria invade tissue and produce findings such as inflammation, purulent drainage, or systemic illness.
The IWGDF/IDSA guidelines emphasize that diabetic foot infection is primarily a clinical diagnosis rather than one based solely on a positive wound culture.
IDSA
Diabetic Foot Ulcer vs. Infected Wound: Key Differences
| Feature | Uninfected Diabetic Foot Ulcer | Infected Diabetic Foot Wound |
| Open skin wound | Present | Often present |
| Bacteria on wound surface | May be present | May be present |
| Spreading redness | Typically absent | May be present |
| Increased warmth and swelling | Not necessarily present | Common findings |
| Purulent drainage | Absent | May be present |
| Deep tissue involvement | Possible without infection | Possible |
| Antibiotics required | No, unless infection develops | Generally yes |
| Wound care required | Yes | Yes |
| Risk of bone infection | Depends on depth and other factors | Increased with deeper or persistent infection |
The appearance of an ulcer alone cannot reliably establish whether deeper infection is present.
How Do Physicians Determine Whether a Diabetic Foot Ulcer Is Infected?
Diagnosis begins with a thorough examination.
Assessing Local Signs of Infection
Clinicians evaluate redness, swelling, tenderness, warmth, and purulent drainage.
The IWGDF/IDSA classification generally identifies a soft tissue infection when at least two relevant local inflammatory findings are present and another explanation is not more likely.
Measuring Wound Depth
Deep ulcers raise concern for infection involving tendons, joints, or bone.
A physician may perform a probe-to-bone examination when osteomyelitis is suspected.
Evaluating Circulation
Poor blood flow can reduce the body’s inflammatory response and make infection harder to recognize.
Vascular assessment is therefore important, especially when a wound is not healing.
Laboratory Testing
Blood tests, including inflammatory markers, may help when infection severity or bone involvement is uncertain.
Tissue Culture
When infection is present, an appropriately collected tissue specimen can help identify the causative bacteria.
Imaging
X-rays may identify bone changes, foreign bodies, or other abnormalities.
MRI is often used when bone infection remains a concern after the initial evaluation.
How Are Diabetic Foot Ulcers Treated Before Infection Develops?
Preventing infection begins with effective ulcer management.
Pressure Offloading
Reducing repetitive pressure is a central component of diabetic foot ulcer treatment.
Specialized offloading devices can help protect the affected area and support healing.
Wound Cleaning and Dressings
Appropriate cleansing and wound dressings help protect tissue and maintain an environment favorable to healing.
The dressing is selected according to the wound’s characteristics, including drainage and tissue condition.
Debridement
Removal of callus and nonviable tissue can help reduce pressure and prepare the wound for healing.
The method and timing depend on circulation and other clinical findings.
Blood Glucose Management
Effective diabetes management supports overall healing and reduces additional complications.
Vascular Evaluation
Patients with poor circulation may need vascular testing and treatment to improve blood flow.
What Changes When a Diabetic Foot Ulcer Becomes Infected?
Once infection develops, the treatment plan must address both the infection and the underlying wound.
Antibiotic Treatment
Mild soft tissue infections may respond to appropriately selected oral antibiotics.
More severe infections can require intravenous antibiotics, surgical treatment, or hospitalization.
Antibiotic selection depends on infection severity, likely organisms, culture results, and patient-specific considerations.
Drainage of Abscesses
An abscess is a localized collection of pus.
When present, an abscess often requires drainage because antibiotics alone may not adequately control the infection.
Surgical Debridement
Moderate or severe infections sometimes require surgical removal of infected or dead tissue.
Urgent surgical evaluation is particularly important when gangrene, deep abscesses, or necrotizing infection is suspected.
Evaluation for Osteomyelitis
An infection extending into the underlying bone requires a different treatment approach.
Some patients can be treated with antibiotics alone, while others require bone surgery combined with antimicrobial treatment.
Learn more about the practice’s diabetic foot infection services and osteomyelitis treatment options.
How Are Diabetic Foot Infections Classified by Severity?
The IWGDF/IDSA system categorizes diabetic foot infections according to clinical severity.
Mild Infection
A mild infection generally involves superficial tissue with limited surrounding inflammation and no systemic illness.
Moderate Infection
A moderate infection involves more extensive local inflammation or deeper tissue structures without the systemic criteria used to classify severe infection.
Severe Infection
A severe infection involves systemic manifestations and requires urgent medical assessment.
The classification helps guide decisions about antibiotics, imaging, surgical consultation, and hospitalization.
Can an Infected Diabetic Foot Ulcer Lead to Amputation?
Yes. Severe diabetic foot infections can lead to tissue destruction, gangrene, osteomyelitis, and limb-threatening complications.
However, amputation is not inevitable.
Timely treatment, appropriate antibiotics, debridement when indicated, improved circulation, pressure offloading, and coordinated specialty care can help preserve tissue and reduce complications.
According to the IWGDF/IDSA guidelines, multidisciplinary care is central to managing serious diabetic foot infections. This includes attention to infection control, vascular health, wound care, and metabolic management.
IDSA
How Can You Prevent a Diabetic Foot Ulcer From Becoming Infected?
Prevention requires consistent monitoring and early treatment.
Inspect Your Feet Daily
Check for cuts, blisters, redness, swelling, calluses, and skin breakdown.
Patients with neuropathy should not rely on pain to identify an injury.
Wear Appropriate Footwear
Properly fitted shoes and protective footwear can reduce pressure and friction.
Avoid walking barefoot, including inside the home.
Seek Early Care for New Wounds
Do not wait for a diabetic foot wound to become painful or visibly infected.
Early wound assessment can identify problems before serious complications develop.
Follow Your Diabetes Care Plan
Blood glucose management, routine foot examinations, and appropriate treatment of vascular disease help reduce risk.
Avoid Home Procedures
Do not attempt to cut away calluses, remove dead tissue, or drain infected wounds at home.
These actions can cause additional tissue damage and introduce infection.
When Should You See an Infectious Disease Specialist?
An infectious disease specialist can help when a diabetic foot ulcer becomes infected, especially if the infection is severe, recurrent, resistant to antibiotics, or involves deeper tissues.
Specialized care can include microbiology review, targeted antibiotic selection, assessment for bone infection, and coordination with wound care, podiatry, and vascular specialists.
Infectious Disease Associates and Travel Medicine provides specialized diabetic foot infection care for patients in Gainesville, Lake City, and surrounding communities.
Frequently Asked Questions About Diabetic Foot Ulcers and Infected Wounds
Is every diabetic foot ulcer infected?
No. A diabetic foot ulcer is an open wound, but it is not necessarily infected. Infection is diagnosed through clinical findings such as inflammation, purulent drainage, and other signs of bacterial invasion.
Can a diabetic foot ulcer heal without antibiotics?
Yes. An uninfected ulcer can heal with appropriate wound care, pressure offloading, circulation management, and treatment of underlying conditions.
How do I know if my diabetic foot ulcer is becoming infected?
Increasing redness, swelling, warmth, tenderness, purulent drainage, or worsening tissue damage can indicate infection. Patients with neuropathy may have little or no pain.
Does a positive wound culture always mean I need antibiotics?
No. Chronic wounds frequently contain bacteria without clinical infection. Culture results must be interpreted alongside examination findings.
Can a diabetic foot ulcer reach the bone?
Yes. Deep ulcers can extend to underlying bone, and an associated infection can cause osteomyelitis. Medical evaluation is necessary when bone involvement is suspected.
How long does it take for a diabetic foot ulcer to heal?
Healing time varies according to wound size, depth, pressure, circulation, and overall health. Some ulcers heal within weeks, while others require months of treatment.
Can a diabetic foot ulcer return after it heals?
Yes. Recurrence is common when neuropathy, abnormal pressure, or other underlying risk factors persist. Preventive footwear and ongoing foot care are important.
Are skin grafts used for diabetic foot ulcers?
Selected ulcers may benefit from skin grafts or tissue-based products after infection, pressure, and circulation issues have been addressed.
When does a diabetic foot ulcer become an emergency?
Emergency evaluation is necessary for rapidly spreading infection, gangrene, severe systemic illness, suspected deep abscess, or signs of sepsis.
Expert Medical Resources
For additional evidence-based information, review the IWGDF/IDSA guidelines on diabetic foot infections, the International Working Group on the Diabetic Foot, the American Diabetes Association, and the National Institute of Diabetes and Digestive and Kidney Diseases’ diabetic foot care resources.
Contact Information
Infectious Disease Associates and Travel Medicine
Gainesville Office
3600 Northwest 43rd St., Suite D-2
Gainesville, FL 32606
Phone: (352) 225-3650
Lake City Office
733 SW State Rd. 47
Lake City, FL 32025
Phone: (352) 225-2650
Website: idtmhealth.com
If you have a diabetic foot ulcer, a nonhealing wound, or signs of a foot infection, contact Infectious Disease Associates and Travel Medicine for specialized evaluation and individualized treatment recommendations.